Select Page
Up to 90% of US COVID Tests Can Be False Positives

Up to 90% of US COVID Tests Can Be False Positives

Up to 90% of US COVID Tests Can Be False Positives

September 21st, 2020

The use of polymerase chain reaction (PCR) testing as a frontline diagnostic tool for COVID is being questioned. These tests provide a positive/negative result for COVID infection, but do not show how much virus a patient has. The amount of virus can make all the difference when it comes to classifying contagious COVID cases.

Testing the RNA sequence of a virus is a complicated task. Even samples infected with the virus do not contain enough of the viral RNA. Thus, amplification is required to multiply and generate enough RNA to be present for adequate testing.

The COVID PCR test uses this exact amplifying mechanism. It involves a series of steps that are repeated over and over, called cycles. These cycles eventually lead to an exponential increase in genetic material (RNA in the case of coronavirus), doubling the amount with each cycle. This means that after 40 cycles (240), there are about 1000 billion copies of RNA.

The problem with PCR testing is that it only provides a yes or no answer, either someone is infected or not. However, it is extremely important to realize that this is a quantitative issue as well. The PCR test does not show how much virus (viral load) someone has.

Simply put, PCR amplifies the RNA sample in a series of cycles. If there is a high viral load, which means the patient is more infectious and contagious, it will be detected in fewer cycles.

PCR Test Sensitivity Greater Than Live COVID Viral Load 

For COVID testing, the appropriate cut-off needed to detect live virus is between 30-34 cycles, as found by a French study. Detecting the virus at <34 cycles indicates that there is enough viral load to be contagious. Detecting the virus at >35 cycles could indicate that there are just genetic fragments of the virus that pose no particular risk (ie. patient has COVID, but is not contagious).

The latter situation has the potential to lead to a high level of false positive test results. Some researchers estimate that this false postive scenario make up to 90% of COVID cases in the US.

Most PCR tests used in the US set the COVID cut-off limit between 37-40 cycles. Remember, the French study above claimed that if a virus sample needs to be amplified more than 34 cycles in order to be detected, then it is not viable and thus the person is neither infected nor contagious. Even the CDC has suggested that it is difficult to detect any live virus in a sample above a threshold of 33 cycles.
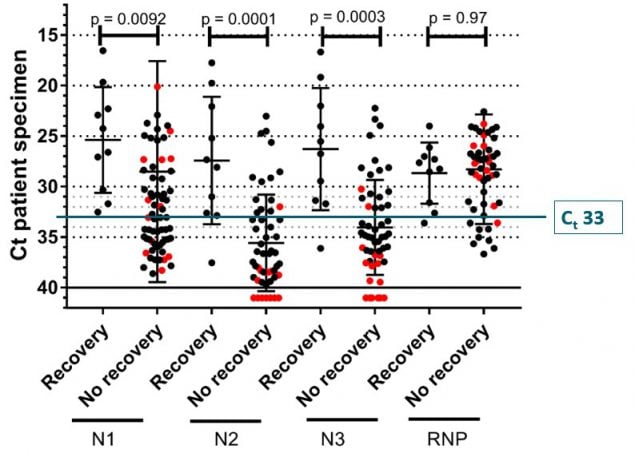
There seems to be a discrepancy between the contagious viral amount needed (~34 cycles) and what PCR tests are diagnosing (~40 cycles). This inconsistency has the potential to result in false positives and inflated COVID cases.

The New York Times reported that in three sets of testing data that modified thresholds under 40 cycles, between 43-90% of positive COVID tests carried viral loads that could be considered non-contagious.

Relying Solely on COVID Case Numbers Is Flawed

The current rhetoric relies on media headlining the number of cases to dictate the severite of the COVID situation. Clearly, with over-sensitive testing, the case numbers alone do not tell the full story. In fact, the case numbers are likely to be inflated and overstating the severity of COVID. Alternative data poins, such as hospitalizations and deaths, must be taken into consideration to reach a more accurate conclusion on the state of disease. 

Greater transparency is needed from the manufacturers of PCR tests and labs that oversee the testing process. The FDA, CDC and overall population need to push for more testing, with multiple thresholds and additional data points. A simple “Yes” or “No” is not sufficient, nor should it be the standard.
Trillium’s CD47 Monotherapy Data Draws Attention of Pfizer and Wall Street

Trillium’s CD47 Monotherapy Data Draws Attention of Pfizer and Wall Street

Trillium’s CD47 Monotherapy Data Draws Attention of Pfizer and Wall Street

September 17th, 2020

Last week, Trillium reported topline data from their latest cohort for TTI-622, the CD47 targeting candidate. The monotherapy data triggered a series of events that followed, which included a $25M investment from Pfizer and a $150M financing from healthcare focused Wall Street funds.

Below is why Trillium’s approach is garnering attention from big pharma and Wall Street.

CD47 Approach Is Interesting Due to Broad Tumor Applicability

A large number of hematologic and solid tumors express high levels of CD47, providing a “do not eat me” signal by binding to signal regulatory protein alpha (SIRPα). This “do not eat me signal” prevents innate immune cells (first line of immune defense; NK-cells, macrophages, to name a few) from attacking tumor cells. Think of CD47 as an evasive tool that tumor cells use to stay off the radar of the immune system.

It is believed that a CD47-blocking antibody will enhance the immune system’s ability to detect tumors that are currently evading the immune system. The rapidly evolving CD47 space has seen an increase in interest recently with big money and big pharma allocating research dollars.

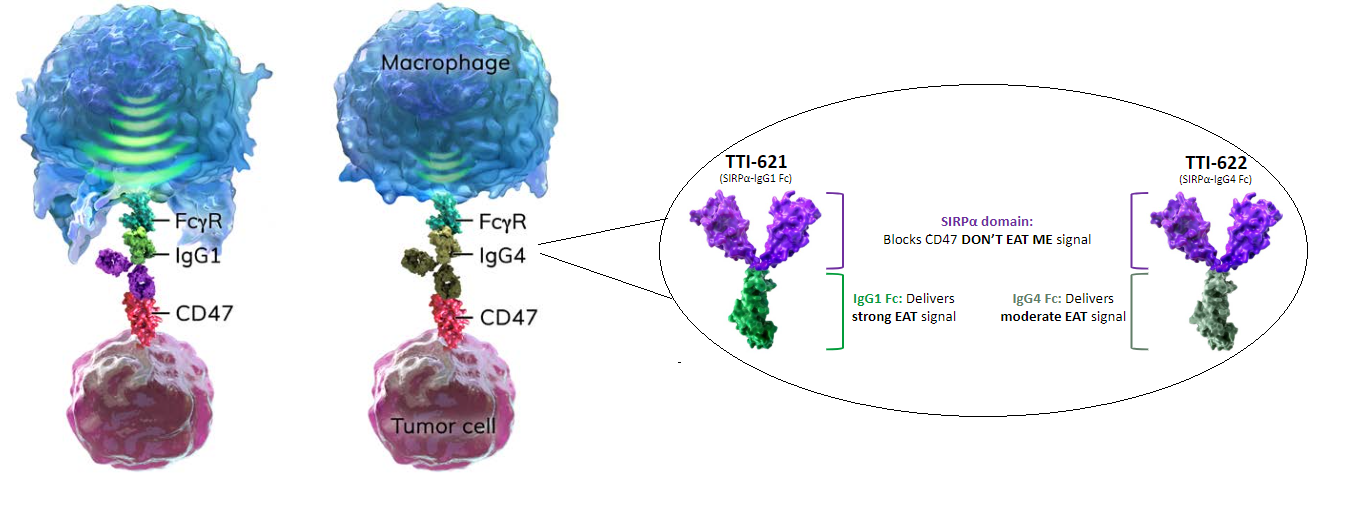
In addition to blocking CD47 through the SIRPα domain, companies are also adding “eat me” signals to enhance the anti-tumor activity. Companies are using different types of antibody isotypes, mainly IgG1 and IgG4, to trigger anti-tumor activity.

Below is a visual representation of a macrophage, representing the immune system defense mechanism, and the CD47 blocking agents that activate the immune system to detect tumor cell.

  • FCγR: FC receptor found on surface of innate cells
  • IgG1 and IgG4: antibody isotypes that deliver the “eat me” signals
  • CD47: “do not eat me” signal found on surface of tumor cell

Gilead’s $4.9 Billion Acquisition of FourtySeven Validated CD47 Space

In early 2020, Gilead struck a deal to buy development stage company FortySeven for $4.9 billion. The takeover gave Gilead control of Phase 1 anti-CD47 antibody magrolimab. FourtySeven had reported 15/39 (38%) overall response rate (ORR) in Diffuse large B-cell lymphoma (DLBCL) patients that had received >3 lines of treatment. Importantly, the response rate was for a combination of FourtySeven’s magrolimab + rituximab. This acquisition kickstarted the interest in CD47 space.

Trillium’s Data Has Best in Class Potential

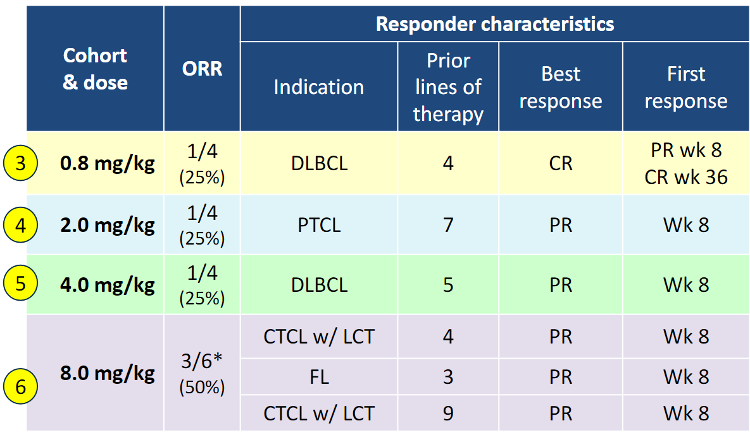
The data that piqued big pharma and healthcare fund interest came from Trillium’s latest cohort reported last week. Cohort 6 (8mg/kg) in relapsed/refractory lymphoma showed 3/6 patients (50%) experienced a partial response (PR). This data was superior to lower dosed Cohorts 3-5 (see below) which had response rates of 25%.

This is an important event for Trillium because these responses are in heavily pre-treated patients (with at least 3 prior lines of therapy) and demonstrate monotherapy activity across a broad range of lymphoma indications. In all Cohorts tested to date, Trillium has shown that 6/18 patients (33%) saw a response. Importantly there were no serious adverse events. The company is now escalating to 12 mg/kg dose level.

It is difficult to make a head-to-head comparison between Trillium and FourtySeven because (1) Trillium’s data is monotherapy, whereas FourtySeven was in combination with rituximab and (2) the indications are different (TRIL in broad lymphomas, FourtySeven in DLBCL).

The main point of interest in Trillium comes from potential response rates when Trillium’s TTI-622 is combined with existing therapies such as PD-1. Theoretically, if monotherapy TTI-622 shows 25-50% response rates in heavily treated lymphoma patients, combination should be higher. This is, most probably, what drew attention of Pfizer and Wall Street.

Not All CD47 Agents Are Equal

From an efficacy point of view, Trillium’s response rate is promising because it is from a single agent, without added benefits of combination approach (discussed above). Importantly, Trillium has reported a relatively clean safety profile.

Although it is overexpressed on tumor cells, CD47 is also expressed in many normal cells, including red blood cells and platelets.  This exposes CD47 antibodies to induce side effects like red blood cell clumping (“hemagglutination”) and anemia, both seen with FourtySeven’s Phase 1 study. Trillium’s candidates, on the other hand, have shown not to bind to red blood cells, which reduces risk of anemia and other blood related adverse events.

The next steps for Trillium are to complete their Phase 1 dose-escalation studies and move on to Phase 2 studies that target specific hematology indications. The good news is that Trillium will have nearly $300 million to advance their pipeline forward.


COVID Kickstarted Telemedicine Adoption With 4,000% Growth

COVID Kickstarted Telemedicine Adoption With 4,000% Growth

COVID Kickstarted Telemedicine Adoption With 4,000% Growth

September 13th, 2020

In 2019, telemedicine was used by less than 10% of Americans. Until then, it wasn’t as popular because most people felt unsure of how to use technology for a doctor’s appointment and quite frankly, didn’t feel the need to replace in-person visits. Regardless, the concept of telemedicine was slowly growing, but the rise of COVID-19, really propelled its widespread use.

One US study held at NYU Langone Health (NYULH), a New York City based healthcare system, collected data from their electronic healthcare record (EHR) system from January to April. The goal was to see how many visits were related to COVID, based on matching related key words (ie. COVID, fever, cough etc.) These visits were then divided into either urgent care or non-urgent care visits.

It was found that virtual urgent care (VUC- purple) numbers increased by over 600% and non-urgent visits (non-VUC- grey) grew by over 4000% (graph below). From March 4th to 19th alone, the amount of telemedicine urgent care visits increased over 16-fold, especially those around 20-40 years old.

There was a substantial increase in those even older than 40 (see table), where it might be assumed that those who are older might have a harder time with the technology associated with virtual care use.

The increased use of telemedicine was seen not only in patients, but medical providers as well. Within the span of 6 weeks, over 150 000 virtual care visits were conducted, with <100 000 of them being unique patients and <2500 unique medical providers.

Interestingly, despite this exponential uptake of telemedicine, the satisfaction of patients remained unchanged. Telemedicine proves to have great benefits, especially during a global pandemic. Since there was a marked turnover of virtual care visits, specifically in the urgent care setting, there was an increased capacity in the emergency room for those who needed it most. For non-urgent care, the increase in telemedicine proved its ease of use, overall satisfaction amongst patients and endorsing of social distancing, one of the limited available interventions against COVID. This transition to telemedicine is also spurring creativity in the way visits are being held and staff is being assigned.

Telemedicine decreases as in-person visits return

Though telemedicine showed great potential during the rise of the coronavirus, numbers have started to decrease as in-person visits become more available. Certain downsides to virtual care also lead to this decline. Due to the fear of contracting the virus, virtual visits may have increased, but some people have forgone being seen by their doctors completely. This can be problematic for those with chronic conditions who need regular check-ups and monitoring. Certain specialities also require parameters that cannot be met through a virtual visit. While general practitioners and mental health specialists may be able to conduct the majority of their visits online, doctors like podiatrists or oncologists may require a physical analysis of the patient for proper diagnosis and treatment.

There is also an idea that telemedicine will reduce the cost of healthcare. However, this claim is being questioned as some doctor’s doubt there will be a large enough turnover of patients to virtual care to reduce the cost of rent and employees’ wages.

Telehealth is here to stay

Regardless of the sudden drop in telemedicine, numbers are still significantly higher than what they were this time last year. It is apparent that an overdue shift in the healthcare system is finally taking place, however the challenge now lies in finding a balance between returning to regular in-person visits and finding which cases can continue to be online.

Overall, this report made clear the impact of COVID on virtual care. A concept that was once aspiring to grow for years, skyrocketed in just a matter of weeks.


Scientists Offering Homemade COVID Vaccines To Anyone Willing To Risk It

Scientists Offering Homemade COVID Vaccines To Anyone Willing To Risk It

Scientists Offering Homemade COVID Vaccines To Anyone Willing To Risk It

September 3rd, 2020

Months prior to the development of any coronavirus vaccine ready enough to enter clinical trials, the founder of a biotech company in the States had been self-administering his own vaccine. He was even publicly promoting his product on Facebook, trying to recruit any participants willing to pay the $400 he charged. Not only was a lawsuit filed against him, he was also confronted by the FDA.

This is not a unique case as several scientists around the world have been experimenting with this idea, claiming that desperate times call for desperate measures. As with most things, there are people for and against the risky work of these scientists. There are supporters who confide in their skillset while skeptics argue that no matter what claims are made, true safety and efficacy can only be tested in clinical trials. Typically, most clinical trials run under the following conditions:

  • randomized: participants are randomly assigned to treatment or control
  • double-blind: neither the researcher nor the participant knows which intervention is being given
  • placebo controlled: a “sugar pill” with no real effect

These specific conditions are put in place to ensure that the testing of newly developed products provide the most accurate results in a way that is safe and ethical for the participants involved.

One scientist however, argued that even traditional drug development begins with testing in animals. He used this claim to compare himself and his supporters as the animals to justify the administration of the vaccine. The problem with these homemade vaccines is not that the scientists are taking it themselves, it’s that they market it with unsupported claims.

This global pandemic has created a lot of panic amongst people and so they are willing to take more risks in hopes of finding a way to protect themselves. It seems as though the scientist who charged $400 per person took advantage of this fear and used it to propel the success of his vaccine. He claims that his vaccine not only offers protection against the virus, but also treats those who are infected.

Such misleading information not only gives people false hope, it also puts them at risk of contracting the virus if they think that getting the vaccine means they can stop taking the proper precautions.

Possibility of COVID Re-infection Doesn’t Seem as Far Off as Once Thought

Possibility of COVID Re-infection Doesn’t Seem as Far Off as Once Thought

Possibility of COVID Re-infection Doesn’t Seem as Far Off as Originally Thought

August 31st, 2020

To date, we know that the body mounts an immune response to COVID when infected. What we do not know, though, is how long this immunity lasts and whether or not it protects from re-infection. Recently, the attention of many has been spiked at the news of a young 25-year old male being infected twice, with two genetically distinct strains of COVID.

Genetic sequencing data showed that the two infection events contained certain mutations that would classify them as distinct strains. However, since the patient was re-infected within a short 2-month timeframe of initial infection, it is unlikely that this can be explained through evolution. Scientists are still unsure of the exact mechanism, but based off of the information to date, it seems that reinfection with COVID is possible, but rare.

Evidence on the relationship between immunity and other strains of coronavirus show that immunity to the disease can be lost within 1-3 years. Public health experts usually expect that if the immune response to initial infection is not enough to protect from re-infection, it would at least dampen the symptoms the second time around.

What is so interesting about the case of the 25-year old male is that, compared to the first time the patient tested positive, his symptoms seemed to have worsened the second time with him even having to be admitted to the hospital for oxygen support.

Immunity Can Be Strong but Not Always Consistent

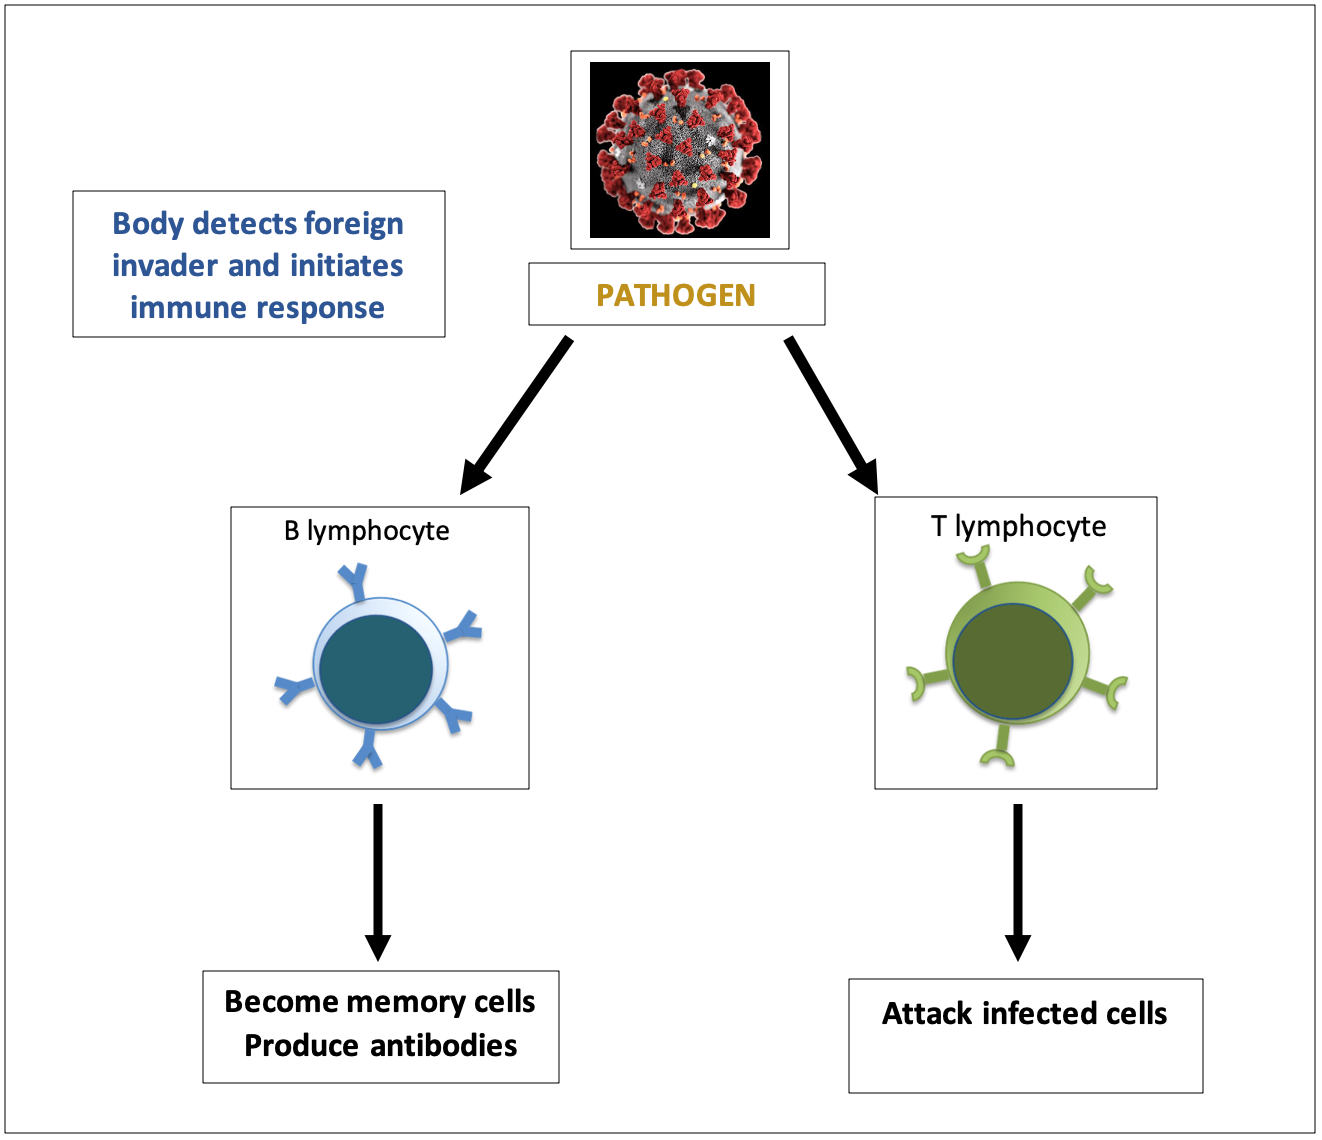
Normally, our immune system fights an infection by providing us with three main soldiers;

  1. Antibodies: molecules that attach to pathogens and block them from causing infection
  2. T-cells: attack infected cells and stop them from spreading
  3. B-cells: produce antibodies and memory cells that strengthen immune response the second time around

Problem is, with a new pathogen like COVID, until more data regarding the mechanism of its re-infection comes along, it is hard to tell how long the body’s immunity against it will last. However, like every mechanism in the body, no two people will have the same response to something. That goes for immunity too. The strong immune response a young healthy individual will mount to any given infection will not be the same as the much weaker one an older individual will produce. The severity of the disease will also produce differing immune responses in infected individuals. Someone with a severe case of COVID will likely produce a much stronger immune response compared to someone with a mild case.

Details regarding someone’s immunity can be seen through blood work. For infections that we are well acquainted with, scientists have a good estimate of what levels of antibodies/T-cells/B-cells need to be detected in the blood to know whether someone is protected. However, with a new virus like COVID, there is not enough data to establish such parameters. Because of this, it is hard to know if we build a strong enough immunity to fight off COVID and if it will last long enough to protect us from reinfection.

Inconclusive data complicates the development of a vaccine

The goal of a vaccine is to deliver a small enough dose of the pathogen to initiate an immune response strong enough to create memory cells. That way, if the individual is exposed to the pathogen at a later time, they will have a strong enough immunity to avoid disease. However, with the data we have so far, it seems as though initial exposure to COVID might not result in complete immunity. This can complicate the development of a vaccine that relies on this concept to be effective.

COVID Cost An Estimated 160x More Than Other Pandemics

COVID Cost An Estimated 160x More Than Other Pandemics

COVID Cost An Estimated 160x More Other Pandemics

August 28th, 2020

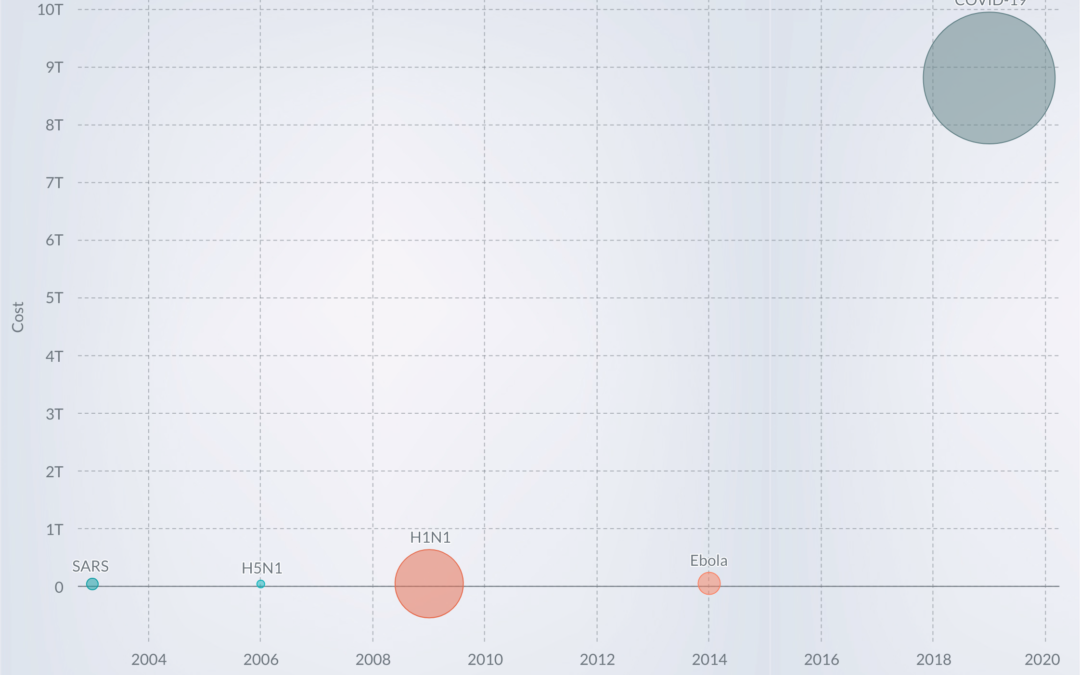
The Asian Development Bank (ADB) estimates that the global economic impact of COVID-19 could be $8.8 trillion. The ADB assumes that this scenario follows a 6-month containment (described below as “Long Containment Scenario”), where travel bans, productivity, and investment cuts last 6 months. The other scenario, a short-term containment, would last 3-months and result in a $5.8 trillion economic impact globally.

The table below shows the GDP impact (in millions $) and GDP (as a % drop from 2018) for each region.

The total impact figure includes health spending as well as shocks to:

  • trade (lower tourism, receipts and trade)
  • production disruptions
  • impaired labor mobility (transport resctrictions, work from home)
  • lower consumption growth
  • weaker investment growth

COVID Cost 160x More Than Ebola & Other Recent Pandemics

2003: SARS – $40 billion (770 death toll)

2006: H5N1 – $40 billion (175 death toll)

2009: H1N1 – $45 billion (200,000 death toll)

2014: Ebola – $55 billion (11,300 death toll)

2019: COVID – $8,800 billion (or $8.8trillion and 830,000 death toll)